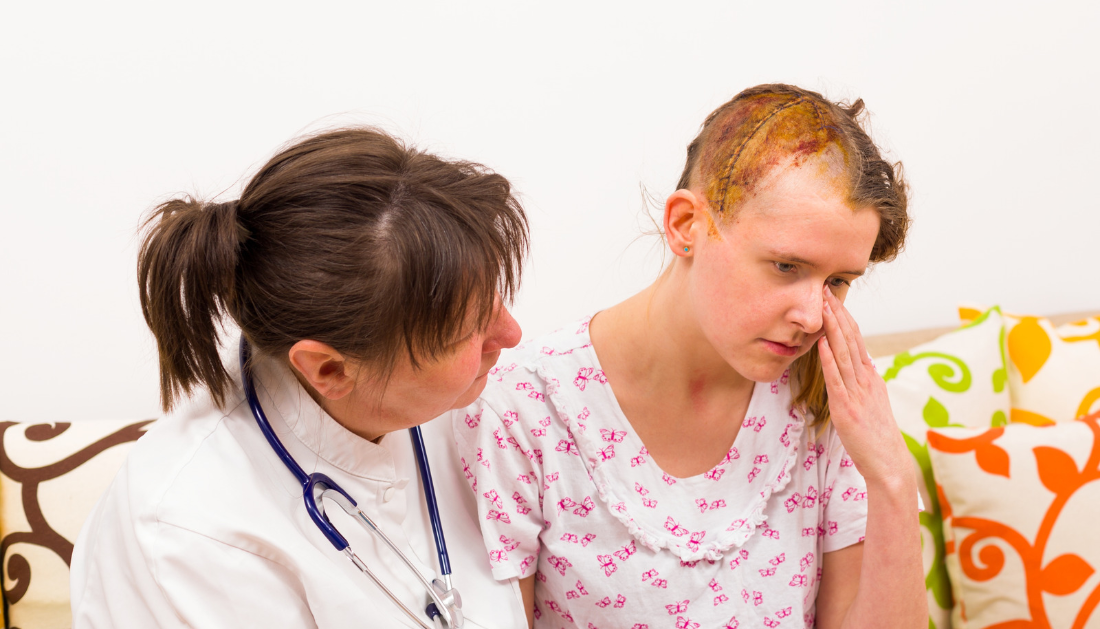
Awake Craniotomy Outcomes and Postoperative Neurological Deficits

A retrospective study found that 30% of patients experienced new or worsening neurological dysfunction within 48–72 hours after awake craniotomy. The findings highlight the need for careful postoperative assessments, as early functional and cognitive changes may not indicate permanent neurological damage.
Awake craniotomy allows neurosurgeons to remove brain lesions near critical language and motor regions while patients remain conscious during essential stages of surgery. However, interpreting neurological changes immediately after surgery remains challenging. A small study published in Chinese Neurosurgical Journal highlights the importance of distinguishing temporary postoperative effects from persistent deficits.
Researchers led by Professor Fang Liu of Nanjing Medical University, China, reviewed 30 patients who underwent awake craniotomy for intracranial lesions involving motor or language areas between January 2019 and November 2024. The team assessed neurological function 48–72 hours after surgery.
Nine patients (30%) developed new or worsening acute neurological dysfunction. 30% of patients had a reduction of at least 10 points in Karnofsky Performance Status (KPS), while 26.7% experienced a decline of at least 2 points in Mini-Mental State Examination (MMSE) scores.
New or worsening motor weakness affected 16.7% of patients, and 10% developed new-onset aphasia. The researchers also reported that 27 patients (90%) completed intraoperative awake mapping. Three patients required conversion to general anesthesia before completing functional mapping.
These findings provide an early snapshot of awake craniotomy outcomes, particularly functional and cognitive changes during the first few postoperative days.
Neurological assessments shortly after surgery can reflect more than surgical injury. Cerebral edema, postoperative fatigue, and residual sedation may influence cognitive performance and functional scores.
Patients who completed awake mapping had a numerically lower rate of acute neurological decline than those who did not: 25.9% aocnea 66.7%. However, this difference may not be clinically meaningful. The researchers also found no statistically significant clinical predictors of acute neurological deterioration.
The study examined survival outcomes as an exploratory analysis. Seventeen patients died during follow-up, and median overall survival was 43 months. However, the small sample, diverse intracranial pathologies, missing information on resection extent and molecular biomarkers, and lack of long-term functional assessments limit interpretation. The absence of a control group also prevents comparisons with craniotomy under general anesthesia.
The findings underscore the importance of interpreting early postoperative neurological deficits within the broader clinical context. Clinicians should assess functional, cognitive, language, and motor changes carefully rather than automatically classifying every early decline as permanent impairment.
The authors call for larger, prospective studies involving more clearly defined patient groups and serial neurological assessments over at least three months. Such research could clarify how frequently early deficits resolve, identify patients at risk of persistent impairment, and inform postoperative counseling and rehabilitation planning.
For neurosurgeons, nurses, and rehabilitation teams, understanding the limitations of early postoperative scores remains essential when evaluating recovery after awake brain surgery.

 EEG Monitoring for Cybersickness: New Study Findings
Key takeaways Researchers at the University.
 Brain-Computer Interface Uses EEG in Unresponsive Patients
Key findings at a glance Mind-controlled.
 Gamma Oscillations Restored in Alzheimer’s Disease Mice
Key takeaways Researchers restored parvalbumin (PV).
 Visual Impairment Linked to Higher Dementia Risk
Key findings at a glance A.
 Epilepsy Drugs May Interact With Hormonal Contraceptives
Key points: Nearly one-third of people.
 Night Shift Work Alters Key Circadian Gene Expression
A recent study published in Frontiers.
 Dietary Polyphenol Intake Associated With Lower MCI Odds
Key Points Older adults without mild.
 Pink Noise Boosts Brain Waste Clearance During Sleep
Key Points Pink noise delivered during.
 Maternal Illness Linked to Epigenetic Fetal Brain Changes
Maternal illness during pregnancy may influence.
 Rett Syndrome: Carotid Body Linked to Breathing Dysfunction
Key Points Rett syndrome is associated.
Leave a Comment